Healthcare SEO writing has to do three jobs at once. Get the medical facts right, so nothing you publish risks patient safety or your E-E-A-T (Experience, Expertise, Authoritativeness, Trust) scoring. Read like something a real patient wants to read, not a copy-paste of a symptom checker. And carry the on-page signals Google uses to rank a page: focus keyword placement, heading architecture, internal linking, and schema. Miss any one of those three jobs and the piece either ranks without converting, converts without ranking, or stalls in legal review before it goes live.
You will get the whole framework here, end to end. How to brief a writer well. How to structure a ranking piece from H1 to FAQ. What word-count band matches each intent type. How to run the medical review step without flattening the writing voice. And the on-page signals every published piece has to emit to reach the top three for its target keyword.
One last frame before the framework. Healthcare content sits inside what Google calls YMYL (Your Money or Your Life), which raises the ranking bar for demonstrated expertise well above what a home services or B2B SaaS site has to clear. That is why the same 2,500-word structure that ranks in home services can stall on page 2 in healthcare when the reviewer credit or the schema is missing. Treat every rule here as a floor for YMYL, not a stretch goal.
SEO content length healthcare, what actually ranks
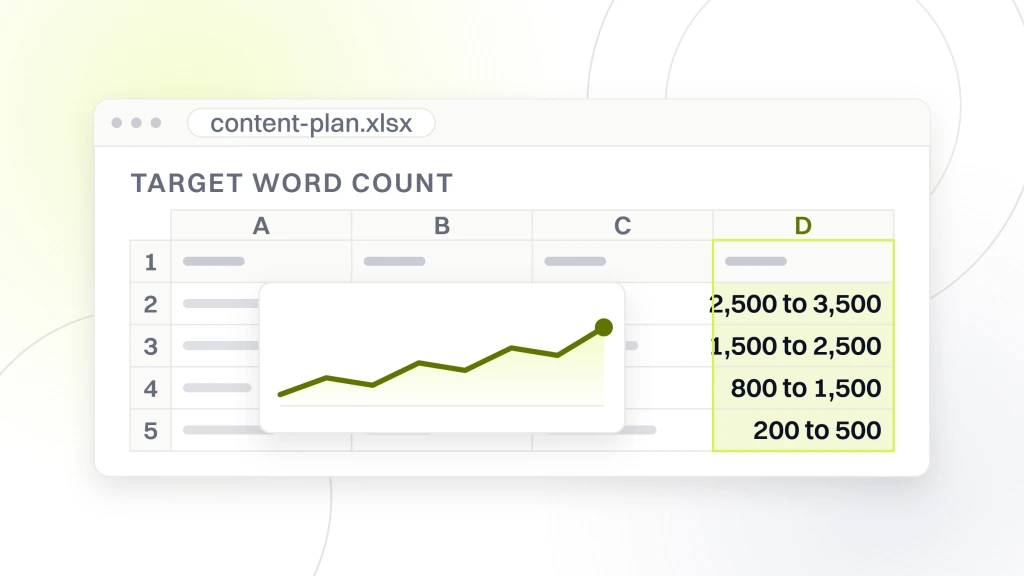
Word count is not the ranking factor. Ranking pages tend to run long so they cover the topic completely. That is correlation, not causation. The right length depends on intent, competition, and topic complexity. Chasing a fixed word count without matching the top-3 SERP length either overwrites or underwrites the page.
| Intent type | Target word count | Section count | Media count |
|---|---|---|---|
| Informational (symptom, condition) | 2,500 to 3,500 | 10 to 14 H2s | 3 to 5 images, 1 to 2 tables |
| Commercial (service, procedure) | 1,500 to 2,500 | 7 to 10 H2s | 2 to 4 images, 1 table |
| Transactional (booking, contact) | 800 to 1,500 | 4 to 7 H2s | 2 to 3 images, 1 table |
| Hub or pillar | 3,000 to 5,000 | 12 to 18 H2s | 4 to 8 images, 2 to 3 tables |
Why long pieces beat short pieces for healthcare
Patients are researching high-stakes decisions. They want depth. Google reads their behavior, time on page, scroll depth, pogo-sticking rate, as a quality signal. A 1,200-word page on “dental implants cost” up against a 2,800-word competitor with better structure ranks lower and converts worse. The depth is not padding. It is answering the follow-up questions patients have without forcing them back to Google for the next detail.
When shorter beats longer
Some queries genuinely warrant short content. Office hours, parking directions, insurance accepted list. Those pages should sit at 200 to 500 words and rank on relevance, not depth. Never over-write a page whose intent is transactional and answerable in one paragraph. The patient just wants the answer. Padding to hit a word count teaches Google the page is bloated and drops the ranking accordingly.
The overwriting risk
Writers chasing a 3,000-word target on a 1,500-word topic pad the page with filler. Patients notice. Bounces go up. Rankings drop. Treat the word count as a band, not a target. Land inside the band based on real topic complexity. Underwriting risks missing the topic; overwriting risks producing pages patients do not finish.
Medical review workflow that supports SEO content guidelines healthcare
Every ranking piece needs medical review before publishing. Not “the marketing lead read it and it seemed fine.” A named clinician has to sign off. That review step is where E-E-A-T signals get their strongest reinforcement, and it is where most content programs stall out if the workflow is not designed for speed.
Who reviews what
Match the reviewer to the topic. Implant content reviewed by an implant provider. Pediatric content reviewed by a pediatric provider. General health content can rotate through the whole clinical team. Batch each reviewer’s pieces into a weekly or monthly slot so the interruption to clinical schedule stays small. Providers who review 4 pieces at once on Thursday afternoon push back less than providers pinged for one piece at a time all week.
What reviewers look for
Give reviewers a two-page checklist. Clinical accuracy on every factual claim. Correct treatment protocol descriptions. Correct medication references. Recovery-timeline realism. Contraindications called out where relevant. No claims that overstate outcomes. No claims that understate risks. That checklist keeps the review focused and produces 30-minute reviews instead of 3-hour rewrites.
How to name the reviewer in the byline
The published piece carries a “Medically reviewed by [Provider Name], [Credentials]” line under the title. That line is a trust signal Google reads, and it is a trust signal patients read. Never publish healthcare content without it. If no provider will sign off, the piece is not ready. Use the review pass as a forcing function for accuracy, not a bureaucratic hoop. See our Healthcare Website Copywriting for the CTAs and voice patterns that pair with the review workflow.
On-page signals every healthcare SEO writer should hit
On-page signals are the mechanical half of the job. Focus keyword placement, heading structure, image alt text, internal linking. Each one is a checkbox item, not a judgment call. A writer who hits all the on-page signals produces pieces that rank consistently. A writer who freelances them produces pieces that rank randomly.
Focus keyword placement
Focus keyword in the H1 (verbatim), the first 100 characters of the intro, at least 2 H2 headings, the meta description, the featured image alt text, and 6 to 12 times through the body at natural density. Never keyword-stuff. Density above 2% flags as spam. The goal is verbatim placement in the anchor positions plus natural inclusion elsewhere, so the page reads clean to patients and clear to Google.
Internal and outbound linking
4-plus internal links: one to the industry hub, one to a service or retainer page, two to sibling cluster posts. 3-plus outbound links to authoritative primary sources (CDC, NIH, medical association guidelines, peer-reviewed research). Every link carries descriptive anchor text. Never link to competitor practices. Never link to affiliate content. See our Healthcare SEO Keywords for the cluster map that dictates internal linking.
Schema for the piece
Every published piece emits Article schema plus MedicalWebPage schema plus, if the page carries FAQ content, FAQPage schema. Provider bylines get Person schema pointing at the provider’s professional profile. Medically reviewed pieces emit reviewedBy pointing at the reviewing provider’s Person schema. Schema is where trust signals get made machine-readable for Google and for the AI systems that now cite health content directly in their answers.
Answer-first paragraphs under every H2
Under every H2, drop a self-contained 40 to 60 word answer paragraph before any elaboration. Google reads that opening as the snippet-ready answer to the heading question and lifts it into featured snippets, People Also Ask, and AI answer boxes. Patients read it and stop hunting. The rest of the section can then deepen the answer with examples, tables, and provider quotes. Skip the pattern and the page gives up SERP real estate a competitor will happily take.
Real numbers from a healthcare content SEO program
North County Dental Care, a Vista, CA family practice of more than 20 years, had thin content spread across unrelated keywords and flat new-patient volume. We rebuilt the site with content written for the clinic’s core services, fixed technical SEO, and ran local SEO and Google Business Profile ads alongside it. The result was 385% organic traffic growth, 500% marketing ROI, and 12 to 16 new patients each month, with 1,000% total patient growth from 2021 to 2024.

Operational takeaway
The writer was not better after the framework. The brief was better. The review was tighter. The structure was locked before writing started. That is the whole change. Output quality is 60% brief, 20% writer, 20% review. Practices that under-invest in the brief and over-invest in the writer keep getting inconsistent results. Our Healthcare SEO Audit covers the audit that flags weak briefs before they become weak pieces.
Hiring and managing a healthcare SEO writer
The market is thin. Fewer writers know the medical vertical than know home services or B2B SaaS. The good ones charge $150 to $400 per piece for well-briefed 2,500-word content, and they book out fast. Practices that hire without a clear brief format burn 3 to 5 writers before landing on one who can execute.
What to test in a paid trial
Pay for one piece against a real brief. Score it on medical accuracy (zero fact-check corrections), voice (patient-voice test), structure (matches brief), and on-page signals (hits every checklist item). Writers who score 8-plus on all four are candidates for a monthly retainer. Writers who score below 6 on any one are not, no matter how good the writing feels on first read. The scoring makes the hire objective and removes gut-call bias from the decision.
Rates and expectations
$0.10 to $0.20 per word for freelance healthcare content. $0.20 to $0.35 per word for writers with medical or clinical backgrounds. Full-time healthcare content leads run $75,000 to $115,000 depending on market and specialization. Retainer agencies typically bundle 4 to 8 pieces a month into a $2,500 to $6,000 monthly rate for a single-specialty practice. Our Healthcare SEO Services covers the full agency retainer model.
Feedback loops that produce better pieces
Give the writer feedback with specifics. “Voice was too clinical in section 3” beats “read a bit stiff.” “H2 outline missed the People Also Ask about insurance coverage” beats “could go deeper.” Specific feedback across 5 to 10 pieces trains the writer to your standard. Vague feedback trains them to guess, and guessing produces inconsistent pieces across the retainer.
Common mistakes in healthcare SEO writing
The mistakes we see most often. Publishing without a named medical reviewer. Chasing word counts instead of top-3 SERP alignment. Freelancing the H2 structure. Ignoring the answer-first pattern under question H2s. And skipping provider quotes when the interview logistics feel hard. Each one is fixable with process, not with a better writer.
No named medical reviewer
The most common mistake. Pieces publish with an “Editorial Team” byline and no reviewer credit. Google’s Search Quality Rater Guidelines call out YMYL (Your Money or Your Life) content without demonstrable expertise as low-quality. Every piece needs a named clinician review credit visible under the title. Without it, the page caps at a ranking ceiling well below what the content could otherwise earn.
Word count over SERP alignment
Writers chase a fixed 2,500-word target regardless of topic. When the top-3 SERP average sits at 1,500 words, the page is padded. When it is 3,500, the page is thin. Word count targets should come from the SERP, not from a house style guide. Read the top 3, average their word counts, add 10 to 20%, and target that band. Match the SERP or the page does not rank.
Freelanced H2 structure
Writers left to build their own H2 outlines produce pages that read like essays. Google’s ranking algorithm rewards structural patterns that match search intent. The brief includes the H2 outline for that reason. Skipping it turns every piece into a fresh restructuring exercise, which slows output and produces inconsistent ranking outcomes across the same retainer.
Skipping the answer-first pattern
Question-formatted H2s (“How much does an implant cost?”) need a 40 to 60 word answer paragraph directly underneath. Google lifts those into featured snippets and “People Also Ask.” AI answer engines pull from the same block. Skip the pattern and the page loses that real estate to a competitor who did include it. That real estate is often worth more than half the organic click-through rate on the SERP.
Closing the loop on healthcare content that ranks
Strong healthcare content is 60% brief, 20% writer, 20% review. Get the brief right, hire against a scoring rubric, run the review workflow with named clinicians, and the pieces compound over time. Skip any one of those three steps and the retainer produces inconsistent output at best. The framework is copyable. The discipline to run it every piece is what separates programs that rank from programs that just publish.
Where to start on your first piece
Pick one target keyword from your cluster map. Read the top 3 SERP results. Draft the 15-field brief. Book a 30-minute provider interview. Write the piece against the brief. Run the medical review. Publish with the reviewer credit under the title. That single-piece proof of concept becomes the template for every piece that follows on the same retainer.
What to measure on the first 5 pieces
Track three numbers across the first 5 pieces. Time from brief to publish (target: under 3 weeks). Revision rounds per piece (target: 1 light round). Ranking position 60 days after publish (target: page 2 or better for at least 3 of 5). Miss any of the three and adjust the brief format, the writer selection, or the review workflow. Hit all three and the program is ready for a 4-piece-per-month cadence.
When to add a second writer
Add a second writer when the first one is booked out and the content plan is behind schedule. Never split pieces across writers just for pace. Voice consistency across the site matters. One writer producing 4 pieces a month against a locked brief produces more consistent site-level voice than two writers producing 2 pieces each. Bring the second writer in only when the volume demand genuinely exceeds one writer’s capacity, and pair them on the same brief format for the first month so voice stays tight.