DSO dental marketing is the multi-location growth function inside a dental support organization that owns 10 to 200+ offices under shared corporate governance. Once a group crosses 10 offices, one template tweak ripples across 40 pages, one ad structure shift redirects spend in 12 markets, and one review workflow change moves the map pack for every office in the same week. The wins scale. The mistakes scale faster.
The American Dental Association reports DSO affiliation among U.S. dentists grew from 7.2% in 2015 to 16.1% in 2024, more than doubling in under a decade. Among dentists under 30, only 25% own their practices. That shift compresses growth expectations onto corporate marketing teams that inherited single-practice playbooks and have to make them scale.
Redefine Web runs dental group marketing programs across groups from 12 to 200+ offices, and the five levers below show up in every account we audit. You will finish with the five levers, the working benchmarks, the 90-day workflow map, HIPAA-safe attribution rules, and one DSO case study that moved cost per call 30% across 50+ offices.
Multi location dental marketing website architecture
Multi location dental marketing lives or dies on the website architecture. A 40-office group needs 40 real location pages ranking in their own city, each feeding the local map pack, and each converting local traffic on the same template stack. The architecture calls you make in month one shape what the marketing program can do for the next 5 years.
URL structure that scales
The pattern most DSOs settle on is /locations/city-state/. A shorter /city-name/ at the root pollutes the top navigation once the group grows past 20 locations. Keep the state slug in the URL, since two Springfields exist. Add state-level index pages once you cross 8 locations in a single state.
Component library for location pages
Every location page runs the same components. A local hero with a photo of the actual office. A doctor block with real photos. Hours, insurance, driving directions, local reviews, service list with local specialization callouts, and CTA. Corporate marketing owns component styling. Location marketing owns component content. That split keeps 40 pages on-brand and locally credible at the same time.
Service page architecture across locations
Every location gets its own city-specific service pages for the top 4 to 8 service lines the group offers. Corporate content teams write the shared service copy. Local editorial adds the location-specific pieces, such as the doctors performing the procedure, technology available on site, and the insurance accepted. This creates 200 to 500 real service pages across the group without duplicate content flags.
Paid ads structure that works across 40 locations
Paid ads inside a DSO dental marketing program pay back when the account structure balances central control with local relevance. Every group we audit runs one of three shapes. Fully centralized, meaning one account and geo-targeted campaigns. Fully decentralized, meaning one account per office. Hybrid, meaning one account with location-specific campaigns. The hybrid wins every time.
One account, location campaigns
The hybrid structure runs one Google Ads account per group with one campaign per location per service line. 40 locations by 4 service lines equals 160 campaigns. That sounds like a lot. It is manageable with campaign templates, shared budgets, and portfolio bid strategies. Consolidated conversion data feeds Smart Bidding across all campaigns, and per-location performance dispersion becomes visible instead of hidden inside a rolled-up account.
Local landing pages per campaign
Every ad campaign points to a local landing page for that location and service. Generic landing pages routing all traffic through the corporate homepage cost 25 to 40% of the conversion. Real per-location landing pages with local phone numbers, local doctors, and local social proof convert dramatically better. Our dental ppc landing pages covers the layout.
Call tracking with dynamic number insertion
CallRail with dynamic number insertion writes the correct location-specific phone number into every ad landing page. Each phone call carries the source, medium, keyword, and location. Conversion events fire back into Google Ads and Meta. Groups running DNI across 40+ locations recover roughly 30% more attributed conversions than groups relying on form-fills alone. HIPAA-safe DNI needs BAAs signed with the tracker vendor and patient identifiers stripped from call recordings before they hit the CRM.
Reviews and reputation at DSO scale
Reviews carry the map pack across every DSO office. The review workflow needs to run centrally to hit steady volume, cadence, and response quality. A group with 40 offices and 40 different review workflows ends up with 40 different star ratings. Standardization pays back inside one quarter.
Central request platform, local response
Deploy a single review request platform across every location. Podium, Birdeye, NiceJob, or a native PMS integration all work if the vendor signs a HIPAA BAA. Set the request cadence to an SMS request 2 hours after checkout and a follow-up email at 48 hours. No more than that. Location front desks stay out of the sending flow. They own the response side, meaning thank you notes, clarifying questions, and escalations of negative reviews to the corporate queue.
Corporate escalation on negatives
Every negative review under 4 stars goes to a corporate escalation queue with a 24-hour SLA. The corporate reputation team drafts the initial response, coordinates with the location on facts, and posts. Location front desks never post the response solo. That single rule prevents the 78% of DSO negative-review PR events that come from an over-emotional local response, and it keeps HIPAA-restricted language out of public replies.
Volume targets per location
Set a monthly Google review target per location of 15 new reviews per month per office at a 4.8+ average. That target moves the average location from 400 reviews to 580 in a year. Groups that hit the target across 40 locations gain 7,200 reviews per year system-wide. Map pack rank, close rate, and organic traffic all move together. Our dental review generation covers the SMS template library.
Attribution and reporting across a 40 location DSO
Attribution decides whether corporate marketing keeps its budget or gets cut at the next board meeting. A group with working attribution moves spend inside the quarter based on real ROI per office. A group with broken attribution runs the same budget for a full year and hopes for the best. Attribution is the least glamorous lever on the list and the highest payoff one.
Conversion event stack
Standardize conversion events across every location. Form submits fire an event. CallRail calls over 60 seconds fire an event. Online booking submits fire an event. Chat handoffs fire an event. Every event flows into GA4, Google Ads, Meta CAPI, and the CRM. Groups that skip CAPI on Meta lose roughly 40% of the visibility the platform gives back to the bidding algorithm.
Location-level ROI dashboards
Build a Looker Studio or Power BI dashboard with one page per location plus a group rollup. Show cost per lead by channel, cost per new patient, close rate, and revenue per location. Corporate marketing meets weekly on the dashboard. Location marketing sees their scorecard monthly. Real budget reallocations happen inside the quarter, not at the yearly plan.
PMS integration and revenue closure
Push closed cases and revenue from the practice management system (Denticon, Dentrix Ascend, Eaglesoft, Open Dental) back into the marketing attribution layer via API or event export. That last mile closes the loop from ad click through to signed treatment plan. Most DSOs skip this since the PMS integration is painful. Groups that solve it stop guessing about which channel drives revenue, and they can defend the marketing budget in PE quarterly reviews with real numbers instead of directional charts.
The benchmarks that tell you where a DSO marketing program stands
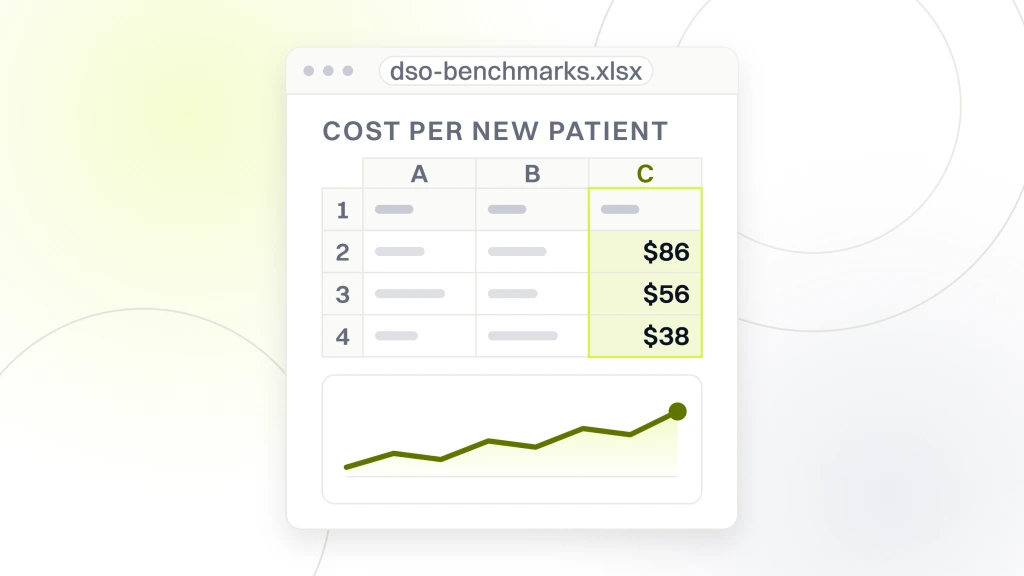
The table below tracks the working benchmarks across dental group marketing programs Redefine Web runs. Read the column that matches your group size and hold it against your current numbers. Wherever the gap is largest, that is the lever to prioritize next quarter.
| Metric | 10-25 locations | 26-75 locations | 76+ locations |
|---|---|---|---|
| Marketing spend per location per month | $4,500 | $3,800 | $3,100 |
| New patients per location per month | 52 | 68 | 82 |
| Cost per new patient | $86 | $56 | $38 |
| Cost per call (Google Ads) | $42 | $32 | $24 |
| Google reviews per location per month | 10 | 15 | 18 |
| Star rating (median) | 4.6 | 4.7 | 4.7 |
| Percent of new patients from digital | 62% | 74% | 81% |
| Percent locations with unified attribution | 55% | 80% | 92% |
Groups sitting below the benchmark on cost per new patient usually have one of three problems. Fragmented ad accounts, generic landing pages, or broken attribution. Groups above the benchmark tend to combine unified ad ops with local landing pages and a working CallRail plus CAPI stack. The percentage of new patients from digital rises with location count. The compounding shared brand and shared SEO investment carries local awareness ahead of ad spend. Marketing spend per location falls for the same reason. Reviews per location per month rise with a centralized workflow. Star rating rises with a corporate escalation queue on negatives.
Every benchmark row ties back to one of the five levers. Track your gap against the column that matches your size, pick the lever with the largest gap, and set a quarterly plan around it. Groups that skip the benchmarking step keep spending on tactics that already worked instead of the tactics that will move the next quarter’s numbers.
Case study Smile Design Dentistry restructuring a 50+ office DSO
Smile Design Dentistry runs 50+ dental offices as a DSO across Florida and the Southeast. When Redefine Web took over the account, inflated ad spend, low-quality leads, and thin tracking were blocking the group’s growth plan. The five levers became the operating framework we ran across every location.

What the audit surfaced
Poor campaign segmentation across locations. Broad targeting mixed high-value implant searches with generic hygiene searches inside the same ad group. No dedicated landing pages by service and location. Underused CallRail, which meant the group could not tell which calls came from ads. Meta was almost entirely silent as a growth channel.
What we restructured
Funnel-stage and geography-segmented campaigns across the Google Ads account. Location-specific landing pages tied to each campaign. Full CallRail deployment with dynamic number insertion. Meta’s first full-funnel paid social program across the group, running video-based engagement into demographic-targeted lead ads. A corporate attribution dashboard that covered every location.
The numbers that moved
Cost per call fell 30% inside 12 months. PPC conversion rate rose 20%. Locations live in the program grew to 50+. Higher lead quality translated into a better close rate at the front desk. Front-desk teams stopped triaging junk leads and started closing higher-value cases. The dashboard the corporate marketing team now runs weekly ties every reallocated dollar back to a real return by location. See the full write-up in our dental marketing for dentists.
The first 90 days of a DSO dental marketing restructure
Restructuring a dental group marketing program is a 12-month arc, but the first 90 days set the trajectory for the whole year. Focus on the highest-payoff moves in this window. Every other project waits until the foundation holds up.
Days 1 to 30: audit and account consolidation
Audit every ad account across every location. Consolidate into a single Google Ads and single Meta account. Migrate call tracking into one CallRail instance. Standardize conversion event definitions across GA4, Google Ads, and Meta CAPI. Map the current attribution gaps. This month sets the measurement baseline everything after depends on.
Days 31 to 60: landing pages and campaign restructure
Build location-specific landing pages for the top 3 to 5 service lines across every office. Restructure campaigns into location-by-service-line ad groups. Deploy DNI phone numbers across every landing page. Restructure Meta campaigns into a real full-funnel flow with awareness, engagement, and lead-gen stages. This month cuts waste and builds relevance in parallel.
Days 61 to 90: reviews, dashboards, and rollup
Deploy the central review request workflow across every location. Stand up the Looker Studio dashboard with location and rollup views. Publish the corporate escalation SOP for negative reviews. Meet weekly on the dashboard and reallocate budget monthly based on cost per new patient by location. Publish the operational SOPs so regional teams know which reports they own and which corporate owns. Our dental marketing plan covers the cadence beyond day 90.
The vendor mix for a modern dental group
A working DSO marketing vendor mix pairs one paid media partner, one SEO and content partner, one review platform, one call tracking vendor, and one analytics stack. Groups that hire 4 paid media agencies to cover 4 regions pay 40% more and get less back. Vendor consolidation mirrors account consolidation. The two decisions move together.
Paid media partner
One Google Ads and Meta partner across the whole group. Look for a hands-on account team, weekly reporting cadence, and a clear track record on multi-location dental accounts. Check for CallRail and CAPI experience. See Google’s multi-location account structure guidance for the target account architecture.
SEO and content partner
One SEO and content partner covers the shared brand site, the location page architecture, and the ongoing content program. Ask for their sample location page template and their content calendar for a DSO client. Vet whether they staff dental-specific writers or generic content writers. Dental accuracy shows up in ranking and trust signals patients notice on the first read.
Review platform, call tracking, analytics
Podium or Birdeye for reviews. CallRail for call tracking. GA4 plus Looker Studio or Power BI for analytics. Check that the platform vendors integrate cleanly with each other and with your PMS. Groups that pick platforms in isolation rebuild integrations 12 months later. Check vendor security posture too, including SOC 2 status, signed HIPAA BAAs, and PMS integration reliability, since the corporate compliance team will ask. Our dental marketing tools covers the compatibility matrix.
Scaling past 100 locations without losing your marketing flywheel
Groups scaling past 100 locations run into a new problem. The flywheel that ran cleanly at 40 offices starts creaking under coordination weight at 120. The five levers still apply, but the operating cadence changes. Corporate marketing shifts from doing the work to orchestrating a regional bench.
Regional marketing leads
Past 60 locations, most DSOs add regional marketing leads owning 15 to 25 locations each. Regional leads run local nuance. Corporate marketing owns brand, tech stack, and reporting. The regional layer becomes the middleware that keeps location-specific relevance alive without slowing corporate governance.
Content ops that scale
Publishing content across 100+ location sites requires a real content operations function. Editorial calendar, tone guide, review workflow, and a queue that moves 30 to 60 pieces per month across the group. Groups that rely on freelancers and no queue stall at 40 pieces per year and lose organic traffic to competitors publishing 3x that.
M and A integration checklist
Every acquired practice arrives with a marketing stack the group has to absorb, migrate, or retire. The integration checklist covers the site migration, GBP re-linking, ad account migration, review platform migration, and CRM merge. Groups that document the checklist cut the average acquisition-to-fully-integrated timeline from 6 months to 8 weeks. See Google’s site move guidance for the SEO half of the merge, and the American Dental Association’s practice management resources for operating context on group ownership.
Turn DSO dental marketing into a growth engine
DSO dental marketing rewards structural discipline. The five levers above compound over quarters, and the groups that run marketing as an operating function (not a rolling series of vendor calls) build market share as competitors slowly plateau. Every dental group we work with hits the same inflection at 12, 40, and 100 offices. The structure resets a little at each inflection, but the core five levers hold. If you run a DSO past 10 locations and want a second look at the structure, book a call with Redefine Web and we will walk the account together.